
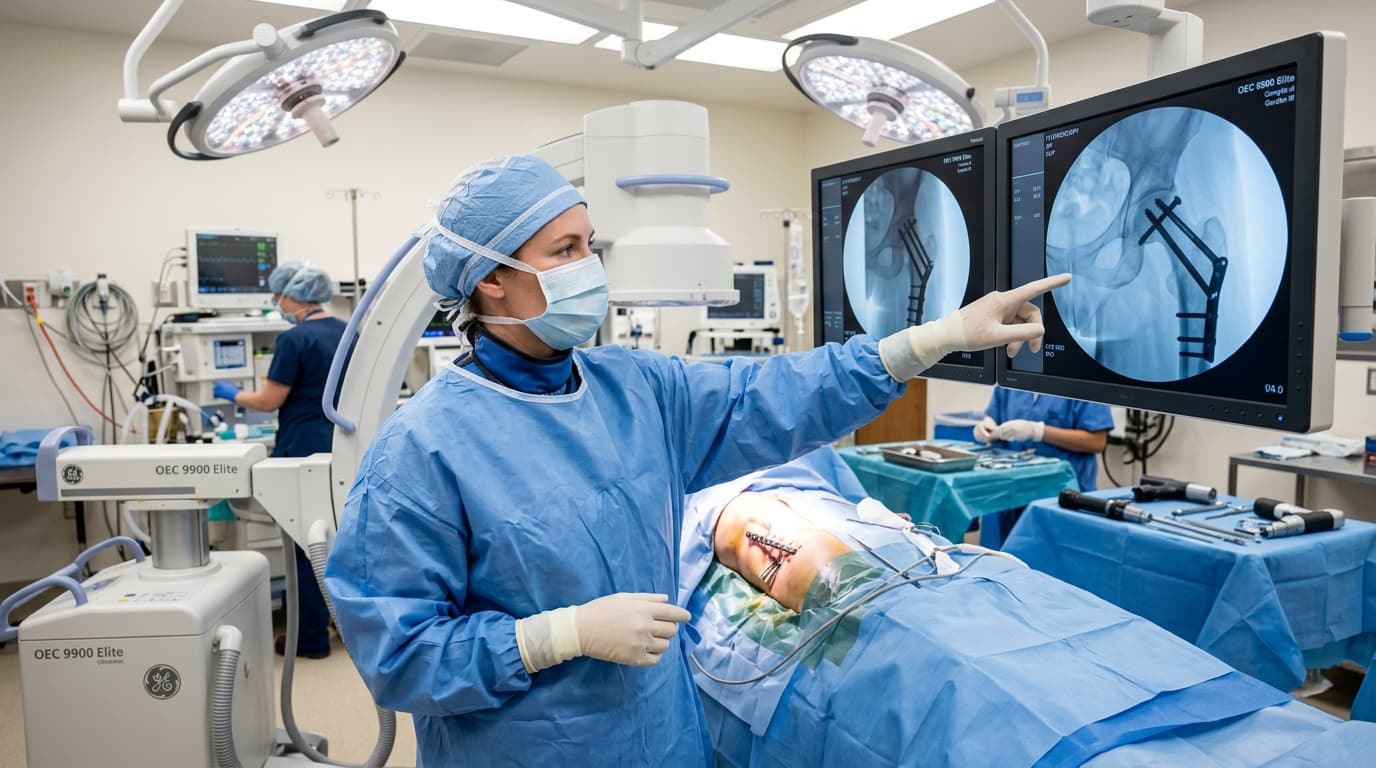

Understanding Complex Hip & Femoral Neck Fractures Care
Hip fractures (femoral neck, intertrochanteric, and subtrochanteric fractures) represent urgent orthopaedic emergencies. In elderly individuals with osteoporosis, minor falls can cause complete fractures, leading to immobility that carries severe risks of pneumonia, bedsores, and blood clots if surgery is delayed. In young adults, high-energy vehicular trauma causes displaced femoral neck fractures requiring anatomical reduction and screw/nail fixation to preserve the femoral head's blood supply. Rapid surgical stabilization within 24–48 hours is vital.
AIIMS Apex Trauma & AO Reconstruction Rigor
Complex articular fractures require anatomical joint surface restoration and stable biological fixation according to international AO principles to prevent post-traumatic arthritis and enable prompt joint mobilization.
When Should You Consider Consultation for Complex Hip Fractures?
Specialist intervention is considered when joint pain or functional limitation significantly disrupts your daily life and conservative measures have been exhausted. Check if you experience any of the following:
Sudden severe hip or groin pain after a fall or motor vehicle accident with total inability to bear weight.
The injured leg appears noticeably shorter and rotated outwards (external rotation).
Severe pain elicited by gentle rotation or movement of the hip.
History of osteoporosis and a sudden fall at home.
Second opinion on complex comminuted intertrochanteric or subtrochanteric fracture patterns.

Dr. Vijay Kumar
Verified SpecialistSenior Consultant Orthopaedic, Robotic Joint Replacement & Complex Articular Trauma Surgeon
“My surgical philosophy centers on biological preservation, anatomical restoration, and rapid functional recovery. By tailoring the intervention to each patient's unique anatomy and lifestyle, we achieve lasting pain relief and active mobility.”
The 4-Stage Precision Clinical Workflow
3D CT Evaluation & Surgical Planning
Rapid pre-operative medical stabilization and echocardiogram/blood clearance.
Direct Anatomical Articular Reduction
Fluoroscopically guided closed fracture reduction on a fracture traction table.
Rigid Internal Fixation (AO Protocol)
Insertion of a titanium intramedullary nail through a 3-cm upper incision, locked with helical blades or screws.
Supervised Early Mobilization & Healing
For displaced femoral neck fractures in seniors: replacement of the broken femoral ball with a smooth modular bipolar prosthesis.
Stage 05: Reconstruction Stage
Multimodal regional nerve block anesthesia allowing immediate pain-free sitting and standing on post-op day 1.
Treatment Modalities Offered
Dr. Vijay Kumar practices conservative joint-sparing protocols first, proceeding to advanced surgical intervention only when indicated:
Non-Surgical & Joint Sparing
- Bed rest is avoided whenever possible due to high medical risks
- Traction splinting used only for temporary pre-operative comfort
Specialised Surgical Procedures
- Minimally Invasive Proximal Femoral Nailing (PFN / PFNA) for intertrochanteric fractures
- Cannulated Cancellous Screw Fixation for un-displaced young femoral neck fractures
- Bipolar Hemiarthroplasty / Total Hip Replacement for displaced elderly femoral neck fractures
- Anatomical Distal/Proximal Locking Plate Fixation for complex subtrochanteric fractures
Recovery Timeline & Mobility Milestones
Day 1: Up out of bed, sitting in a chair, standing and walking with walker support.
Days 2–3: Independent room walking, comfortable discharge home with home physiotherapy plan.
Weeks 4–6: Transition from walker to single cane; progressive hip abductor strengthening.
Weeks 8–12: Solid bone union confirmed on X-rays; unassisted independent ambulation.
International Fellowship & Surgical Suite Records

Intraoperative kinematics & 3D navigation alongside Japanese surgical faculty.

International fellowship-level precision applied to patient care in Patna.
Frequently Asked Questions on Complex Hip Fractures
Prolonged bed rest in seniors causes life-threatening complications (pneumonia, bedsores, blood clots, muscle wasting). Surgery stabilizes the broken bone immediately, allowing the patient to sit up and walk the next day.